

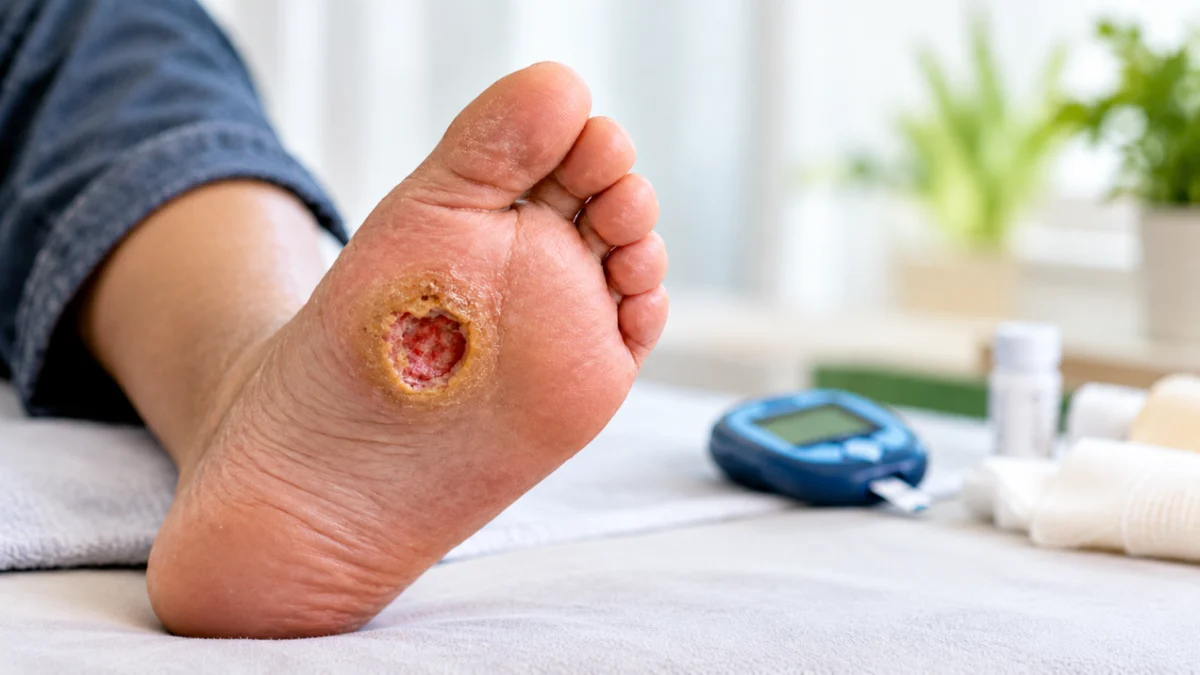
A seemingly minor wound on the foot can escalate into a life-altering infection for individuals with diabetes, with potentially devastating consequences reaching as far as the bone. This concerning progression, known as osteomyelitis, transforms a localized issue into a systemic threat, underscoring the critical need for vigilant care and prompt medical intervention.
For millions living with diabetes, the everyday challenges of managing blood sugar levels are compounded by a heightened vulnerability to foot complications. Reduced sensation, impaired blood circulation, and elevated glucose levels create a fertile ground for infections to take hold and spread with alarming speed. While a small cut or blister might appear innocuous, for those with diabetes, it can be the harbinger of a serious medical emergency. This article delves into the critical question: can an infected diabetic foot ulcer spread to the bone, and what are the implications when it does?
Drawing on expert insights from Dr. Rajiv Kovil, a Diabetes & Obesity Specialist at Zandra Healthcare, and addressing a pertinent query posed on the public forum Quora, we explore the insidious nature of diabetic foot infections, the tell-tale warning signs, and the complex treatment pathways, including the potential necessity of surgical intervention.
The Alarming Trajectory: From Skin to Bone
The answer to whether a diabetic foot ulcer can spread to the bone is a definitive and concerning, "Yes." Dr. Rajiv Kovil unequivocally states, "An infected diabetic foot ulcer can gradually spread from the skin into the deeper tissues and eventually reach the bone." This process is medically termed osteomyelitis, and it represents one of the most serious and feared complications arising from a diabetic foot ulcer.
The insidious pathway of infection is a stark reminder of the interconnectedness of the body’s systems. Bacteria, originating from the ulcer, can migrate through the subcutaneous fatty tissue, progressing into the fascia, tendons, muscles, and joints, before finally breaching the bone itself. Dr. Kovil highlights that ulcers that are deep or have persisted for a significant duration are particularly worrisome, especially those situated over "bony prominences" – areas where the bone is close to the skin’s surface.
"Once infection becomes deep, pus, tissue destruction and swelling can increase pressure within the foot and further compromise blood supply," Dr. Kovil explains. This creates a vicious cycle: increased pressure restricts blood flow, hindering the body’s ability to fight the infection, while the unchecked infection leads to further tissue damage and swelling. Without immediate and effective treatment, this cascade can rapidly escalate, jeopardizing the toe, the entire foot, or even the limb, and in the most dire circumstances, posing a threat to the patient’s life.
Understanding the Vulnerability: Why Diabetes Amplifies Risk
The heightened susceptibility of individuals with diabetes to severe foot infections stems from a confluence of physiological factors, often exacerbated by the chronic nature of the disease.
Diabetic Neuropathy: The Silent Saboteur: A primary culprit is diabetic neuropathy, a form of nerve damage that commonly affects the feet. This condition diminishes sensation, meaning individuals may sustain injuries like blisters, cuts, or pressure sores without feeling any pain. Unaware of the damage, they may continue to bear weight on the affected area, exacerbating the wound and creating an entry point for pathogens.
Peripheral Arterial Disease (PAD): Impaired Healing: Compounding the issue is poor circulation, often a consequence of peripheral arterial disease (PAD). PAD narrows or blocks the arteries that supply blood to the limbs, significantly reducing blood flow to the feet. This compromised circulation not only delays wound healing but also hampers the immune system’s ability to deliver crucial cells and nutrients to the site of injury, making it harder to fight off infections.
Hyperglycaemia: A Hindrance to Healing: Dr. Kovil points to the broader impact of high blood sugar levels: "Hyperglycaemia and associated medical problems can further interfere with the body’s response to infection and healing." Elevated blood glucose levels can impair the function of white blood cells, which are vital for combating infections, and can also contribute to inflammation and damage to blood vessels.
Masked Symptoms: The Deceptive Absence of Pain: A particularly insidious aspect of diabetic foot infections is that they may not always present with overt, dramatic symptoms. "Fever and chills may be absent even with significant infection," Dr. Kovil notes. This lack of a clear, immediate signal can lead to a dangerous underestimation of the severity of the problem, allowing the infection to progress undetected.
This unfortunate combination of unnoticed injuries, delayed healing due to compromised circulation and blood sugar control, and the potential for subtle symptom presentation creates a perilous environment where even a seemingly minor foot ulcer in a person with diabetes demands immediate and serious attention.
Heeding the Alarms: Recognizing Signs of Bone Involvement
The progression of a diabetic foot ulcer to the bone is not an overnight event, but it can advance with alarming speed if left unaddressed. Recognizing the warning signs is paramount for timely intervention and preventing catastrophic outcomes.
Visible and Palpable Indicators
- Increased Redness, Warmth, and Swelling: A spreading area of redness, a sensation of increased warmth around the wound, or significant swelling are all indicative of an escalating infection.
- Pus or Discharge and Foul Odor: The presence of pus, any unusual discharge, or a foul-smelling odor emanating from the ulcer are clear signs of bacterial activity and potential deep-seated infection.
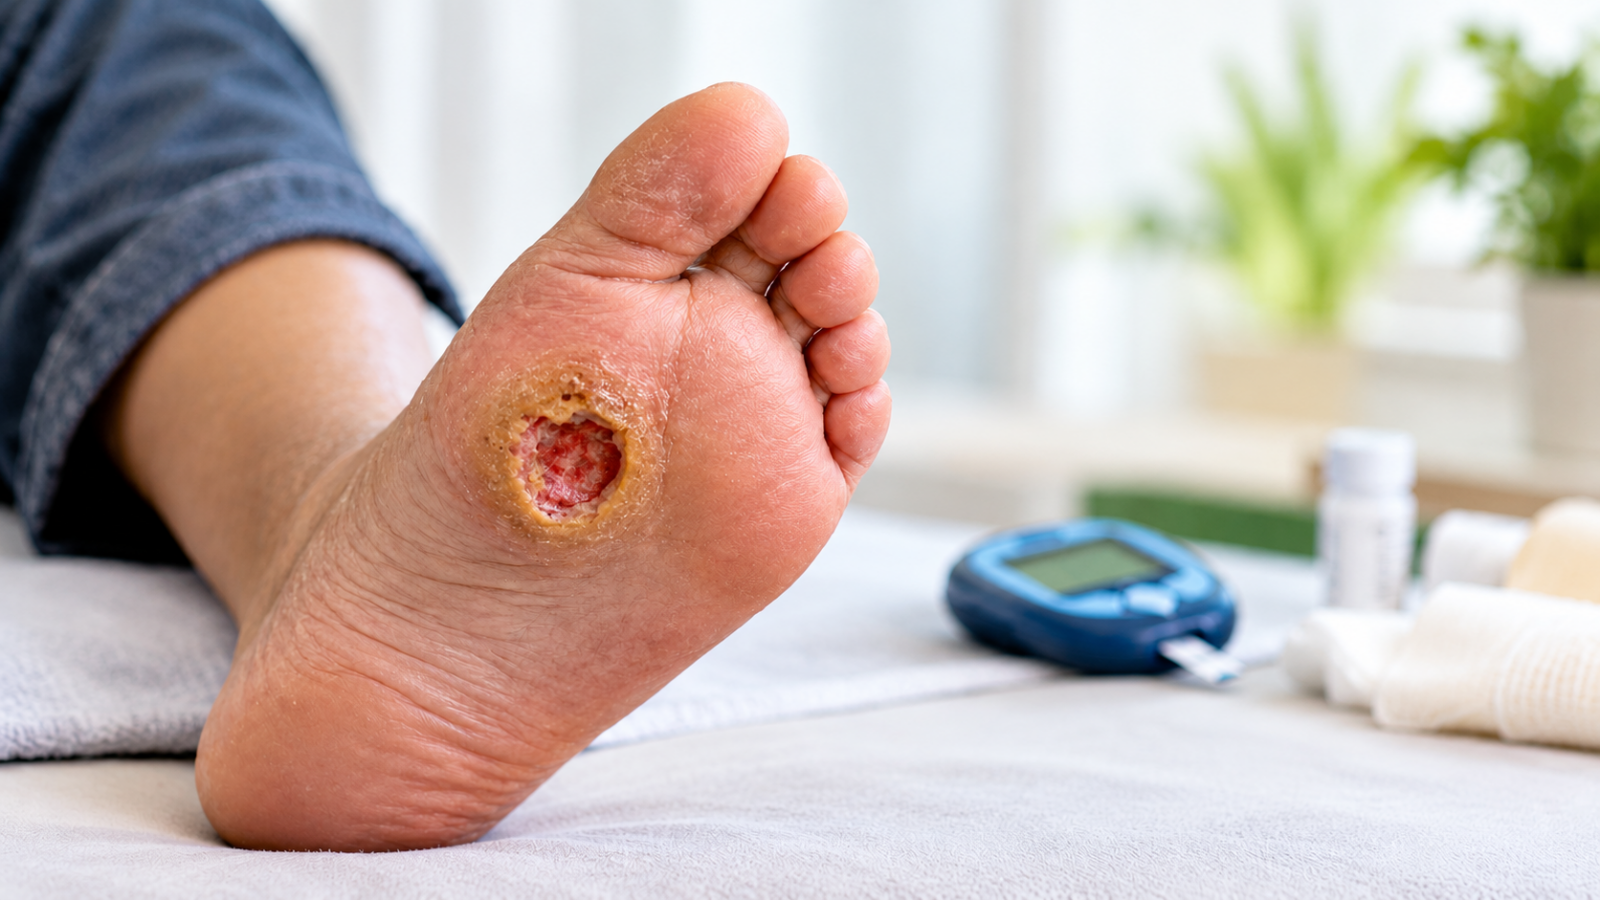
- Ulcer Growth and Depth: An ulcer that is visibly increasing in size or depth, or if the surrounding tissue begins to turn dark or necrotic (dead), signals a worsening condition.
- Spreading Redness: Redness that extends beyond the immediate vicinity of the ulcer can indicate that the infection is actively spreading through the tissues.
- Swollen, Red Toe: A swollen and red toe, even if not directly at the site of the ulcer, can be an important, albeit sometimes overlooked, clue to a deeper infection.
The Critical Probe: Direct Evidence of Bone Involvement
Dr. Kovil emphasizes the significance of direct observation: "A deep ulcer, visible bone, or bone that can be felt with a sterile probe raises suspicion of osteomyelitis." The "probe-to-bone" test, a crucial diagnostic tool, involves gently inserting a sterile, blunt probe into the ulcer. If hard, gritty bone is felt, it significantly increases the likelihood of bone infection.
Systemic Clues and the Neuropathic Challenge
While pain can be a sign of infection, its absence does not guarantee that the infection is mild. Diabetic neuropathy can severely blunt pain perception, meaning a person might not feel the increasing discomfort associated with bone infection. Therefore, other systemic indicators become vital:
- Fever, Chills, and Weakness: While not always present, the onset of fever, chills, or marked weakness can signify a more severe systemic infection.
- Worsening Blood Glucose: A noticeable and unexplained worsening of blood glucose control can also be a red flag, indicating the body is under significant stress from infection.
- Gangrene and Rapidly Spreading Redness: The appearance of gangrene (tissue death due to lack of blood supply), rapidly spreading redness, a deep abscess, or clear signs of severely impaired circulation demand immediate medical attention as they may indicate a limb- or life-threatening infection.
The Diagnostic Gauntlet: Pinpointing Bone Infection
When the clinical signs suggest a potential spread of infection to the bone, a multi-faceted diagnostic approach is employed to confirm osteomyelitis and guide treatment.
Initial Clinical Assessment and Bedside Tests
The process begins with a thorough clinical evaluation. Doctors meticulously assess the ulcer’s size, depth, and overall severity. They meticulously examine for any signs of infection, such as redness, swelling, warmth, and discharge. Critically, the blood supply to the foot is evaluated to understand the potential for healing and the impact of infection on circulation.
The probe-to-bone test, as mentioned earlier, is a key bedside diagnostic tool. Its ability to directly detect bone is invaluable in raising suspicion.
Imaging and Laboratory Investigations
-
Plain X-rays: "The recommended initial investigation combines this clinical assessment with a plain X-ray and inflammatory markers such as ESR or CRP when appropriate," states Dr. Kovil. X-rays can reveal changes in the bone, such as bone erosion or swelling, that are indicative of osteomyelitis. However, it’s crucial to understand their limitations: "Importantly, an early X-ray can sometimes be normal, so a normal film does not completely exclude osteomyelitis." Early bone infection might not yet manifest as visible changes on an X-ray.
-
Advanced Imaging (MRI, PET, Bone Scan): When uncertainty persists after initial assessments, advanced imaging techniques become indispensable. Magnetic Resonance Imaging (MRI) is often the preferred modality due to its superior ability to visualize soft tissues and early bone changes. Positron Emission Tomography (PET) scans or bone scans can also be utilized in specific clinical scenarios to detect areas of increased metabolic activity, suggesting infection or inflammation in the bone.
-
Cultures for Organism Identification: Identifying the specific bacteria causing the infection is crucial for selecting the most effective antibiotic therapy. While superficial wound swabs can provide some information, "a bone specimen obtained under sterile conditions for culture is preferred to a superficial wound swab" for suspected bone infections, according to Dr. Kovil. This ensures a more accurate identification of the causative organism.
The Treatment Landscape: Beyond Antibiotics and Towards Intervention
The management of diabetic foot osteomyelitis is complex and hinges on the extent of the infection, the patient’s overall health, and the availability of adequate blood supply. While antibiotics form the cornerstone of treatment, surgery plays a vital role in many cases.
Antibiotic Therapy: The First Line of Defense
"Selected cases of diabetic foot osteomyelitis can be treated with antibiotics without removing the infected bone," Dr. Kovil explains. Current guidelines, such as those from the International Working Group on the Diabetic Foot (IWGDF) and the Infectious Diseases Society of America (IDSA), support a conservative approach in specific situations.
This non-surgical management is particularly considered for:
- Forefoot Osteomyelitis: Infections in the front part of the foot.
- Absence of Peripheral Arterial Disease: Adequate blood flow to the foot is essential for antibiotic delivery and healing.
- No Exposed Bone: When the infected bone is not visible through the ulcer.
- No Immediate Need for Drainage or Deep Infection Control: Cases where there isn’t an abscess requiring drainage or a rapidly spreading deep infection.
When non-surgical treatment is pursued, it typically involves a course of appropriate systemic antibiotics, often lasting for approximately six weeks.
The Surgical Imperative: When Intervention is Necessary
Surgery becomes an essential consideration when the infection is more severe or widespread. Dr. Kovil outlines the critical indications for surgical intervention:
- Dead or Extensively Infected Tissue or Bone: When significant portions of the bone or surrounding soft tissues are necrotic or heavily infected.
- Abscess Formation: The presence of a localized collection of pus requires surgical drainage.
- Gangrene: Tissue death necessitates debridement or removal of the affected area.
- Necrotising Infection: A rapidly spreading and destructive bacterial infection.
- Compartment Syndrome: A dangerous condition where swelling within a muscle compartment restricts blood flow.
- Severe Infection: When the infection is overwhelming and poses an immediate threat.
- Significant Ischaemia: Critically poor blood flow to the limb.
"Blood supply must always be assessed; where circulation is inadequate, vascular assessment and sometimes revascularisation are crucial," Dr. Kovil emphasizes. If the blood supply to the foot is compromised, procedures to restore blood flow may be necessary before or in conjunction with surgical removal of infected tissue.
The goal of surgery is to eradicate the infection while preserving as much functional foot and limb as possible. However, in dire circumstances where the limb or life is severely threatened, "Major amputation is reserved for situations where the limb or life is seriously threatened," a somber reality that underscores the critical importance of early detection and treatment.
Broader Implications: A Call for Vigilance and Comprehensive Care
The potential for diabetic foot ulcers to escalate to bone infection carries profound implications, extending beyond the immediate medical crisis. It highlights the absolute necessity of a multi-faceted approach to diabetes management, encompassing not only blood sugar control but also proactive foot care and early intervention for any signs of damage.
The journey from a minor wound to osteomyelitis is a stark illustration of how chronic conditions can silently erode health if not meticulously managed. The compromised sensation and circulation that characterize diabetes create a unique set of challenges, demanding a heightened level of awareness from both patients and healthcare providers.
For individuals with diabetes, this translates to:
- Daily Foot Inspections: Regularly examining their feet for any cuts, blisters, redness, or swelling.
- Proper Footwear: Wearing well-fitting shoes and socks that do not cause pressure or friction.
- Prompt Medical Attention: Seeking immediate professional evaluation for any foot wound, no matter how small.
- Adherence to Treatment Plans: Diligently managing blood sugar levels and following medical advice for any existing complications.
For the healthcare system, it underscores the need for:
- Enhanced Diabetic Foot Screening Programs: Regular, comprehensive foot assessments by trained professionals.
- Multidisciplinary Care Teams: Collaboration between endocrinologists, podiatrists, vascular surgeons, infectious disease specialists, and wound care nurses.
- Patient Education and Empowerment: Equipping individuals with diabetes with the knowledge and tools to actively participate in their foot health management.
The threat of osteomyelitis serves as a powerful reminder that seemingly minor issues in individuals with diabetes can quickly evolve into complex, limb-threatening conditions. By fostering a culture of vigilance, promoting proactive care, and ensuring timely access to specialized treatment, we can mitigate the devastating consequences of diabetic foot ulcers and safeguard the health and well-being of those living with this chronic disease.
Disclaimer: This article is based on information from the public domain and expert insights. It is intended for informational purposes only and does not constitute medical advice. Always consult with a qualified health practitioner for any health concerns or before making any decisions related to your health or treatment.
